
Choosing Between Fully Ablative and Fractional Laser Resurfacing
Clinical studies show both fully ablative and fractional lasers improve photoageing and scarring through controlled dermal remodelling. Many skin concerns respond well to laser resurfacing, but not every laser is designed to do the same job. The right approach depends on what we are treating, how quickly you need to recover, your skin type, your risk profile, and how much change you want from a single session.
At Midland Skin in Birmingham, your assessment and treatment are carried out by a medical specialist experienced in laser treatment. We work across a full range of technologies in one clinic, including UltraPulse CO₂, UltraClear 2910 nm, Sciton Erbium:YAG 2940 nm, Halo hybrid fractional, and complementary platforms for redness and pigment. That breadth lets us tailor the resurfacing plan around you.
First principles: how these treatments differ
Fully ablative CO₂ or Erbium resurfacing
Removes the entire surface layer of skin in the chosen area and a measured portion of the dermis to trigger full regeneration. Best suited to etched lines, advanced photoageing, and deep textural change where comprehensive collagen renewal is required. Typical recovery to new surface skin is about 7–10 days, followed by redness that can last up to 3-6 months. Safest for lighter skin types (Fitzpatrick I and II). Usually a single treatment is required and the effects can last for several years, although some stubborn areas may need a second session. Limiting factors include the possibility of demarcation lines and post-inflammatory hyperpigmentation.
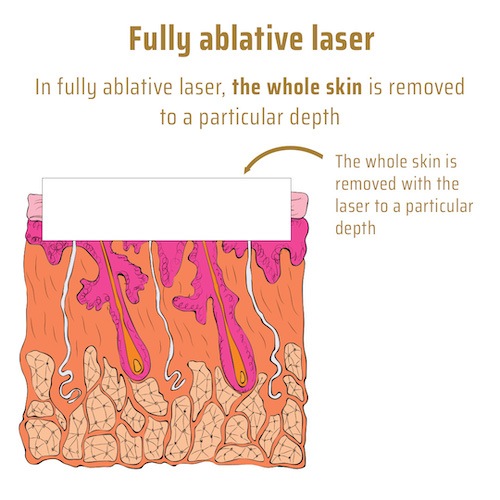
- Further information on fully ablative laser resurfacing: Fully ablative laser resurfacing.
Fractional ablative resurfacing (CO₂, Erbium:YAG and 2910 nm)
Treats a pattern of microscopic columns while leaving bridges of untouched skin to speed healing. Depth and density can be adjusted for acne scarring, lines, pores and texture. Recovery usually takes 5–9 days and is shorter than fully ablative resurfacing. Because only a fraction of the skin is treated, side effects are fewer than with fully ablative resurfacing. Treatment is typically repeated for optimal results. For rejuvenation, plan 2 sessions about 8 weeks apart. For acne scarring, plan sessions about 12 weeks apart.
Fractional CO₂ and Er:YAG lasers deliver columns of thermal injury that stimulate collagen production while leaving surrounding skin intact, allowing faster recovery (Manstein et al, 2004). The degree of improvement and downtime depend on the energy, density, and number of passes used.
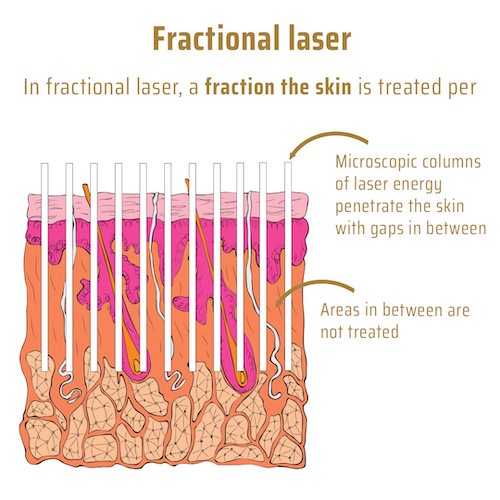
- Further information on fractional laser resurfacing: Fractional laser resurfacing.
Fractional non-ablative resurfacing (for example Halo 1470 nm)
Heats the dermis to stimulate collagen without removing the surface. Useful for early photoageing, fine textural change and maintenance when downtime must be minimal. Usually planned as a course of 3–5 treatments.
- Further information on Halo hybrid fractional laser: Halo laser.
CO₂ or Erbium for ablative work?
- CO₂ tends to give stronger tightening and wrinkle softening because of greater thermal effect.
- Erbium (2940 nm and 2910 nm) ablates very efficiently with less residual heat, which can mean a quicker return to normal barrier function and potentially lower pigment risk when used appropriately. Heat can be increased to emulate CO₂ where suitable.
Comparing the three approaches
| Fully ablative | Fractional ablative | Fractional non-ablative | |
|---|---|---|---|
| Suitable skin types | I–II | I–V | I–V |
| Typical sessions | 1 | 2–3 | 3–5 |
| Time to new surface skin | ~7–10 days | 5–9 days | 0–4 days |
| Social downtime | 14–21 days | 5–10 days | ~5–7 days |
| Swelling | 3–6 days | 1–3 days | 1–2 days |
| Weeping | ~3 days | ~1–2 days | Unlikely |
| Pain after procedure | 1–2 days | 0–1 day | 0–1 day |
| Redness | 3–6 months | 2–6 weeks | Days to 2 weeks |
| Lines of demarcation | Possible | Less likely | Unlikely |
| Grid marks | Unlikely | Occasional | Unlikely |
| Post-inflammatory hyperpigmentation | Possible | Possible | Possible |
| Sun protection essential | 6-12 months | 3-6 months | 3 months |
Everyone heals at their own pace. Allow enough time to heal without pressure.
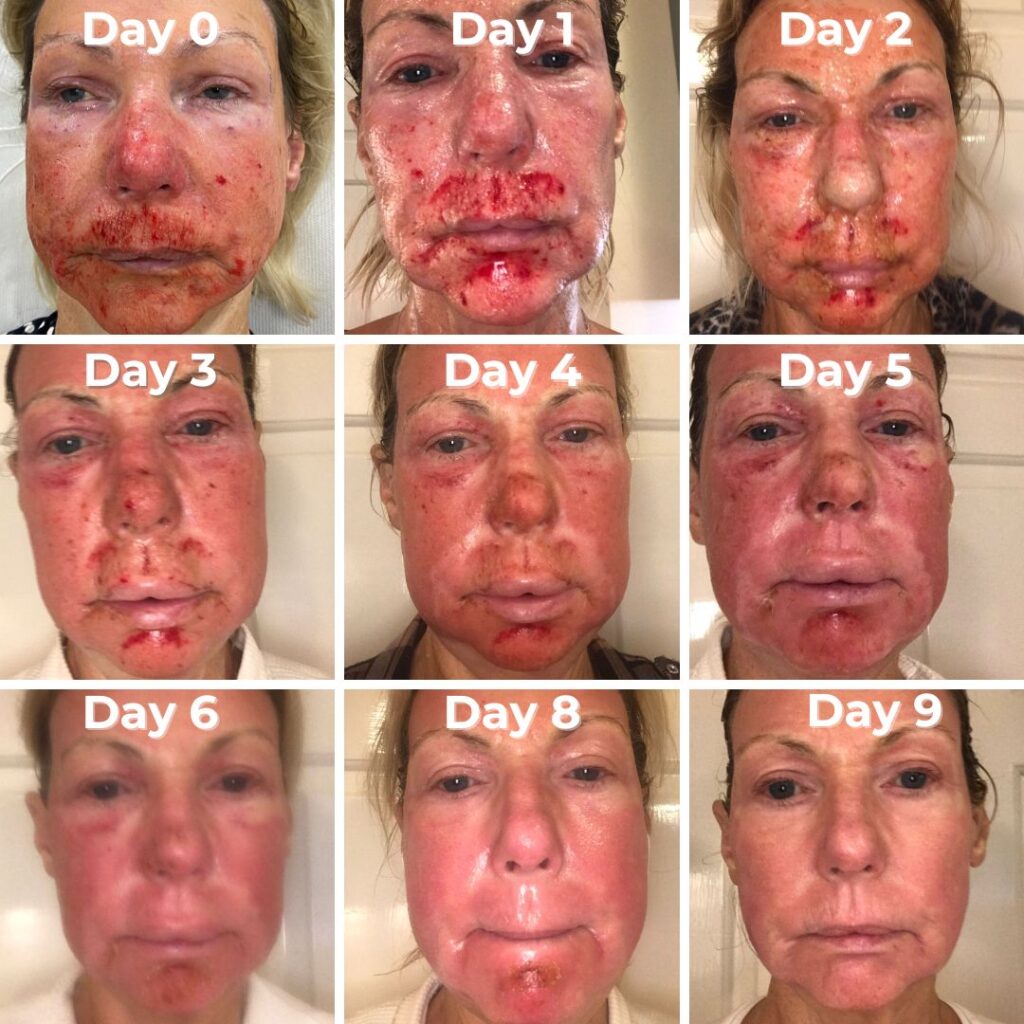
Fully ablative laser resurfacing healing diary
This patient took about 9 days for the skin to reform, and about 2 weeks before she was able to work from home or start going out.
Fractional ablative laser resurfacing healing diary
This patient was ready for work in 7 days from treatment having a moderate density fractional ablative laser.
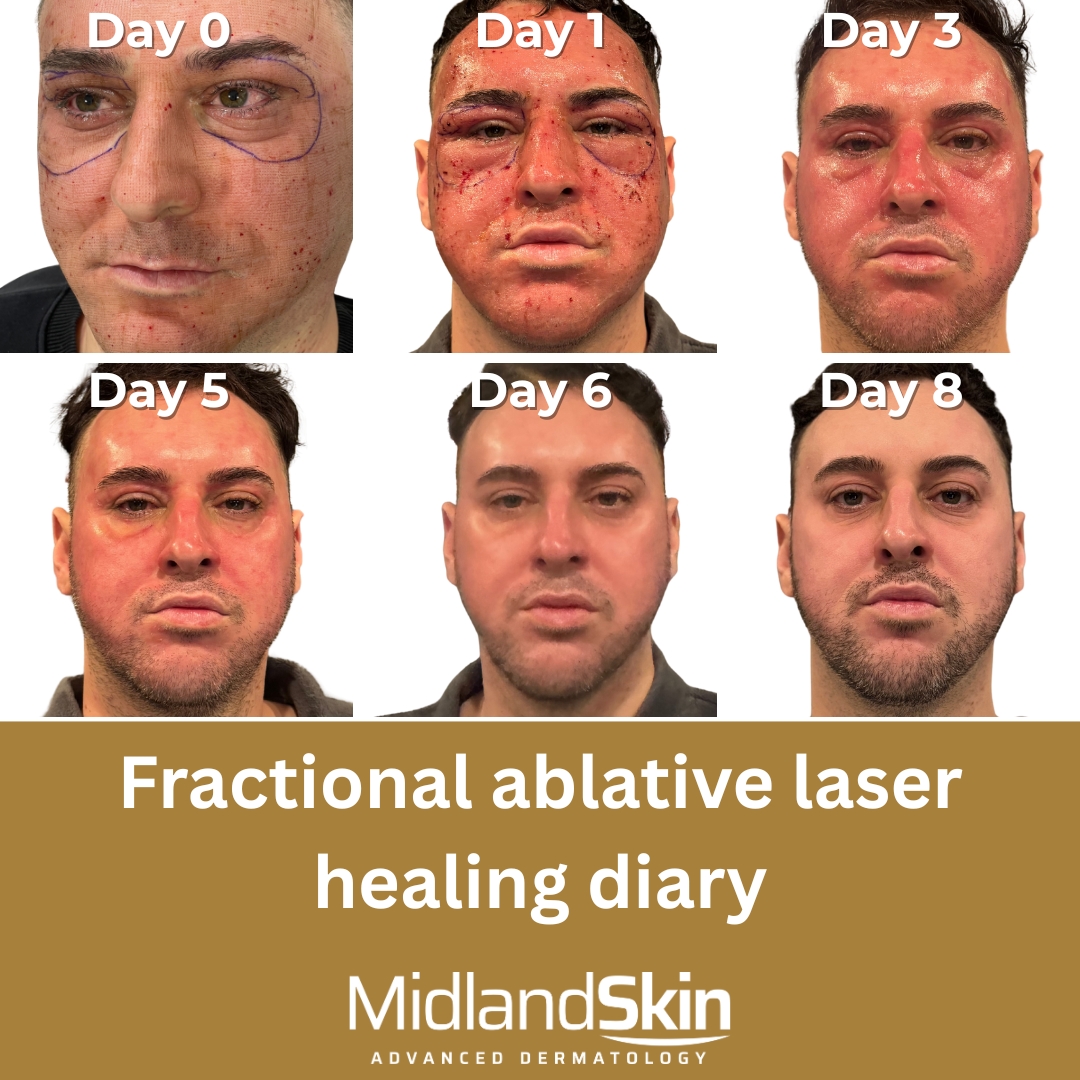
This patient had a lighter fractional ablative resurfacing and was mostly ready by day 5:

What results can you expect?
- Severe etched lines, wrinkles, eyelid laxity, solar elastosis: Fully ablative resurfacing remains the most powerful single procedure in lighter skin types. Fractional ablative approaches also achieve meaningful softening with less recovery time when fully ablative is not appropriate or desired. For example, a 62-year-old woman with skin type II, etched upper-lip lines, solar elastosis and eyelid ageing would typically be offered fully ablative resurfacing with CO₂, Erbium, or both combined. A 33-year-old woman with skin type I and early eyelid ageing would more likely be offered two sessions of fractional CO₂ around the eyes, with light resurfacing to the face.
- Acne scars (rolling, boxcar and mixed): Fractional CO₂ and fractional Erbium both improve atrophic scars. We often combine with subcision, TCA CROSS and, where appropriate, volume restoration. A 24-year-old man with skin type V and acne scarring might be treated with fractional CO₂, Erbium:YAG, UltraClear or Halo.
- Pores, texture and dullness: Fractional Erbium or hybrid fractional options refine texture with steady gains in brightness, plumpness and evenness. A 29-year-old man with skin type III seeking maintenance and brightness would suit Halo or UltraClear.
- Pigment and redness as part of photoageing: Often managed with staged care, using fractional CO₂ or fractional Erbium resurfacing alongside targeted pigment or vascular treatments such as BBL. A 49-year-old woman with skin type IV seeking rejuvenation with limited downtime would suit UltraClear, or Halo with BBL.
- Reducing actinic damage: Ablative resurfacing, both fully ablative and fractional, removes sun-damaged surface skin and has been shown to reduce actinic keratoses in photodamaged skin, with the effect lasting for years after a single treatment. Longer-term follow-up also suggests fewer non-melanoma skin cancers in treated skin. This applies to ablative resurfacing rather than non-ablative treatments.
Skin of colour and pigment-risk planning
Safe laser resurfacing in darker skin types is possible with the right device, parameters and aftercare. Fractional Erbium and low-density fractional CO₂ may be used in darker skin types (Fitzpatrick III–V) with conservative energy and longer recovery intervals. CO₂ remains highly effective too in darker skin types, and selection and aftercare are critical.
Is laser resurfacing worth considering for you?
Laser resurfacing may be worth discussing if:
- Fine lines and etched wrinkles – particularly around the eyes and mouth, where creams have plateaued
- Acne scarring – rolling, boxcar or mixed atrophic scars
- Texture, pores and dullness – where the skin surface has lost smoothness and light reflection
- Sun damage and photoageing – including uneven pigment and actinic change
- Previous treatments have not gone far enough – peels, microneedling or skincare have helped but not delivered the change you want
- You can plan around the recovery – with realistic time set aside for healing
- You want a specialist opinion on which option fits – rather than a single device chosen for you
How we choose which laser
Map the problem
Are the concerns etched lines, mixed acne scarring, or general photoageing?
Match the tool
Pick CO₂, Erbium or hybrid fractional based on area, depth and skin type.
Set parameters
Adjust coverage and depth to balance risk profile, skin type and downtime.
Plan the journey
One definitive session or a staged approach, with clear aftercare and check-ins.
Combination treatment
Combination protocols (e.g. fractional + fully ablative spot treatment) can balance impact with healing, and are supported by histological studies of depth-controlled ablation.
Safety, preparation and aftercare
- Consultant-led planning: Treatment depth is matched to the goal and to delicate anatomy around the eyes and lips.
- Cold-sore prevention: Antivirals are used where there is a history of herpes simplex.
- Pigment-risk preparation: Careful aftercare to reduce post-inflammatory hyperpigmentation.
- Healing support: Regular cleansing, bland occlusive emollients, and strict sun avoidance. Prescription products are introduced if clinically indicated.
- Possible side effects: Temporary redness, swelling, crusting or bronzing, milia, acne flares and pigment change. Infection and scarring are uncommon with good selection and aftercare but remain important risks we discuss in full.
Frequently asked questions
Will this help movement-related lines?
Lasers improve surface lines and texture. Dynamic lines caused by muscle movement usually respond better to targeted injectables. Combination plans are common.
How quickly will I see results?
Freshening is seen within weeks of healing. The full collagen response can take 3–6 months.
Can you guarantee results?
No medical treatment can guarantee a particular outcome. It is important to have realistic expectations. A small number of people may not respond as well as hoped.
How long will the improvement last?
Structural gains from ablative resurfacing are long-lasting. Skin will continue to age, so good skincare, sun protection and occasional maintenance help preserve results.
Can I combine treatments?
Yes. For acne scarring we often combine subcision, fractional laser and TCA CROSS. For photoageing we may add targeted vascular or pigment treatment.
References used for this article
- Manstein D, Herron GS, Sink RK, Tanner H, Anderson RR. Fractional photothermolysis: a new concept for cutaneous remodeling using microscopic patterns of thermal injury. Lasers Surg Med. 2004;34(5):426–438.
- Hantash BM, Bedi VP, Kapadia B, et al. In vivo histological evaluation of a novel ablative fractional resurfacing device. Lasers Surg Med. 2007;39(2):96–107.
- Iyer S, Friedli A, Bowes L, Kricorian G, Fitzpatrick RE. Full face laser resurfacing: therapy and prophylaxis for actinic keratoses and non-melanoma skin cancer. Lasers Surg Med. 2004;34(2):114–119.
About the Author
This page has been written and/or medically reviewed by Dr Sajjad Rajpar, Consultant Dermatologist and Medical Director of Midland Skin, Birmingham.
Dr Rajpar is on the GMC Specialist Register in Dermatology and has over 20 years’ experience in clinical dermatology. He provides clinical oversight to ensure the information on this page is accurate, balanced and consistent with current dermatology practice.
Dr Sajjad Rajpar
Date last updated: 28th Sep 2026

Book in with us
Expert, consultant led care in dermatology, skin surgery, eyelid surgery, lasers and aesthetics.

